


Present-day psychiatry believes that mental illness results from disordered brain biology at levels that are presumably the same in people of all races and ethnic backgrounds. 1
Joseph Metzl, The Protest Psychosis. How Schizophrenia Became a Black Disease
What are the consequences of living without an alternative reality? For decades, biological psychiatry has offered explanations (DSM disorders) and solutions (Big Pharma) as “reality.”
BIRTH-AND-DEATH
My son was born in the winter of 2017. It was midnight on Friday the 13th and their was a bright full moon upon the blackened sky. Let’s just say I was anxious as I stared out the hospital room window. My son was born a few minutes after midnight. At the time of his birth, I was so relieved that he arrived that Saturday morning rather than Friday night. The former meant we would receive an extra day of health insurance coverage in the hospital.

Four years later I would read Mark Fisher’s triumphant book Capitalist Realism: Is There No Alternative? It was a time period where I was studying economic theory and consequently being annoying at social gatherings (“Ain’t Capitalism Awful?”). I realized soon after reading Fisher’s text that he had died by suicide. In 2021, I reviewed his Wikipedia page. The date of his suicide jolted me: January 13, 2017.
The exact same day Fisher took his own life, I assisted (barely) in supporting the birth of life. Upon realizing this odd synchronicity, I wondered what the time of death was for Mark Fisher. I am embarrassed to write that I really wanted to know the specific timestamp because I knew my son’s time of birth. When did Fisher succumb to self-inflicted violence? When did he affix a noose to his neck? I even Googled it. The interest stems from several suicides in my family history as well as my own close encounters with self-destruction.
CAPITALIST REALISM
Fisher articulated how capitalism is “reality” for us. The system has become so pervasive that it hides in plain sight: the instantiation2 of capitalism. It is reflected and refracted across all aspects of our being. The saying goes that it is harder to imagine the end of capitalism than to imagine the end of the world.
Capitalism is at the center of all social processes and the social is now intertwined with capital, e.g., Meta (Facebook). We literally cannot even ponder capitalism being substituted for a different economic system. This is the concept of capitalist realism. Therefore, no one needs to advocate for capitalism because it is everywhere and nowhere in existence. In a sense, capitalism blinds us with its invisibility.
MENTAL HEALTH vs. MENTAL ILLNESS
I believe the widespread embrace and market frenzy over “mental health” is creating a mutation similar to capitalist realism. Let us call it psychiatric realism: one cannot imagine an alternative way of understanding human beings outside of the bio-psychiatric model.
The model used by biological psychiatry is the Diagnostic & Statistical Manual (DSM), which buttresses the neurological or brain-based paradigm. The instantiation of American psychiatry and specifically the biochemical explanation of “mental illness” has created a new “reality.” This is a similar cultural mutation as capitalist realism, because there is no mention in mainstream culture of an alternative understanding. It is “reality.”
The concept of “mental health” has largely replaced the notion of “mental illness.” With the latter it was understood that the illness was causing functional deficits, e.g., social, occupational, legal. The person was unwell. The new emphasis on “mental health” continues the artificial split between a person having a body and a separate mind. Furthermore, abstracting mental health divides it from overall “health.” This is done with individualistic implications.
The new paradigm of mental health suggest that the individual is capable of improving themselves in isolation. The possibility is not the eradication of an “illness” but rather an imperative for self-optimization: “I need to work on my mental health.” This implies that the person learns to better adapt to the capitalist system. Therefore, clinicians help people to get to a point where they—according to Freud—can tolerate the misery of everyday life. 3
Therefore, this transition to “mental health” is capturing something in the culture and not “reality.” And it now implies a moral and more so economic responsibility to address one’s own “mental health.”
The antiquated view of “mental illness” being equated with a moral failing has been resurrected. If one’s “mental health” is not in a constant state of pharmaceutical or talk therapy then it is the person’s own damn fault! Get off the couch and log into Betterhelp to be “your best self.” I’m sure the underpaid, disillusioned, and disembodied therapist will “help” you.
THE DIAGNOSTIC & STATISTICAL MANUAL (DSM)
As a psychotherapist since 2008, I have been trained to administer the Diagnostic & Statistical Manual (DSM) to diagnose patients. 4 Since 1952, the DSM has undergone five different iterations plus revisions. The claim of each update is that the classification system is becoming increasingly scientific, objective, and culturally sensitive. As an analogy, the idea is that psychiatrists are “discovering” disorders like a scientist would find a new species in a rainforest.
The roots of the DSM are anything but inclusive. The DSM is a cultural construction, which implies that it is shaping existing constructions (diagnoses) based on underlying cultural assumptions. The foundation of the DSM is based on an ethnically Northern German person who is gendered male with a cultural and religious Protestant background. The emphasis or ethos is rationality.5 All of that is baked into the system that has been universalized across the globe. The major issue for all the DSM’s is the necessity of the individual to be in control:
Psychiatric treatment, pharmacological or psychotherapeutic, explicitly seeks to assist in regaining the ideal of ‘control’. Control is necessary for, and a sign of, mental health and moral rectitude. 6

DSM I (1952) was a small booklet with something like 26 distinct disorders. It was used to determine the stats of mental illness in the population. There was a major psychodynamic influence (psychoanalysis, including the Unconscious). Psychic problems were understood as being “reactions” to life problems. In 1968, the DSM II bloomed to 100 disorders. The number of diagnostic sections went from two to ten with a child and adolescent section added.7 DSM II utilized multiple theoretical orientations (not solely the Freudian view) and dropped the label of “reactive.”

THE DSM REINFORCES THE “REALITY” OF THE SYSTEM
In the tumultuous 1960s, American psychiatry was moving away from psychosocial understandings of illness and toward biology. The antipsychiatry movement was gaining steam and people were challenging the idea that homosexuality was an “illness.”
Recall that 1968 was a year of radical political movements, subversion, and cultural change. People of color were protesting their colonial enslavement. At the same time the DSM-II was redefining the concept of “schizophrenia.” The new DSM description of the illness incorporated the racist tropes about Black men in the U.S. The criteria and application of schizophrenia as a diagnosis focused on the aggressive and violent madman. Therefore, dark-skinned males who were anti-imperialists were labeled “crazy.”
From the 1960s onward, patients described by doctors as African American, paranoid, delusional, and violent had disproportionately high chances of being diagnosed with schizophrenia. Patients described as white, tearful, sad, ruminative, and harmless, meanwhile, had disproportionately high chances of being diagnosed with mood disorders or anxiety states. 8

The DSM-III is the text I have studied most closely. I nearly fell into despair reading The Making of the DSM-III. The short version is that a bunch of narcissistic, euro-descended, men debated and advocated specific “disorders” to be included in the text. This was done largely to advance their own psychiatric careers, e.g., passive-aggressive personality disorder. And they found ways to hide “homosexuality” as a mental illness within their bible. 9

During the making of the DSM-III, Black psychiatrists requested that racism be listed as a “mental illness.” The head of the DSM-III task force, Robert Spitzer, obfuscated. He reported that the bigot is not “mentally ill” because there is no subjective sense of distress for the racist. Racism is an obvious intersection of cultural constructionism, politics, and mental health that biological psychiatry has repeatedly evaded.
The 1980 DSM-III had to make American psychiatry hegemonic and therefore the discipline had to be “scientific” (depoliticized).10
the move in the direction of biological explanations was motivated by psychiatry’s need to rationalize and justify the growing use of pharmacological intervention. 11
The best way to do that was to create a mechanistic system of symptoms, descriptions, and checklists. The aim was to establish a standardized interview that could be automated. 12
DSM-III sought to eliminate competing explanations implicitly and explicitly contained in previous classifications (i.e., psychological, psychosocial, psychoanalytic). 13
The aim of DSM-III was to eradicate the psychodynamic notions of illness because it implicated the empire. The head of the task force, Robert Spitzer “began to think of ways of “offsetting” the opposition of the psychodynamically oriented psychiatrists.” 14 Spitzer had worked at IBM prior and was attempting to automate diagnoses with computer programs. How humane.
The 1994 DSM-IV reconfigured the previous edition. DSM-IV only added two disorders and made attempts at recognizing culture. Asperger’s syndrome and bipolar II disorder were the additions. The former was understood as a mild form of autism and it is what scores of American children are being diagnosed with under the DSM-5 heading of “autism spectrum disorder.” The new term is much more elastic, which is why the numbers are skyrocketing. It is not because of vaccines or food dyes as RFK Jr. is claiming. Bipolar II disorder is the same as bipolar I disorder (formerly manic depression) except the person’s manic symptoms are not as heightened and problematic.
The term is “hypomania,” and the duration is shorter (days of symptoms versus weeks to months). The depressive episodes are understood as the same in bipolar I and II. I know this because I spent several years exhibiting my own story of manic depression. 15 The DSM-IV task force members have since noted that those two disorders became immensely popular diagnoses.

The distinction between bipolar I and bipolar II disorder is utterly subjective. The latter is a psychiatrically manufactured category.16 In a sense, bipolar II is a product of late-capitalism, which defines and then treats the disorder with more capitalism, i.e., Big Pharma pharmaceuticals. By the time the DSM-5 was released in 2013, I had mastered the application of the psychiatric system. I remember working at a counseling center when the DSM-5 was released. None of the clinicians asked if we should use the DSM-5; they asked when we would start using it.
Classification is neither a reflection of natural facts nor class attempts at social control. Rather, psychiatric nosologies appear as historical cultural creations. They provide standards to live up to and measures for assessing culturally constructed selves in their life worlds. 17

Even if the diagnostic system is “scientific,” as the discipline claims, it erases the social and cultural causes of suffering. Mark Fisher (2009) recognized that this “ruling ontology” largely rejects a social cause of mental health issues. The biochemical explanation rests on the notion that you are your head. Furthermore, a neurological and neurochemical fixation is “commensurate with its depoliticization.”
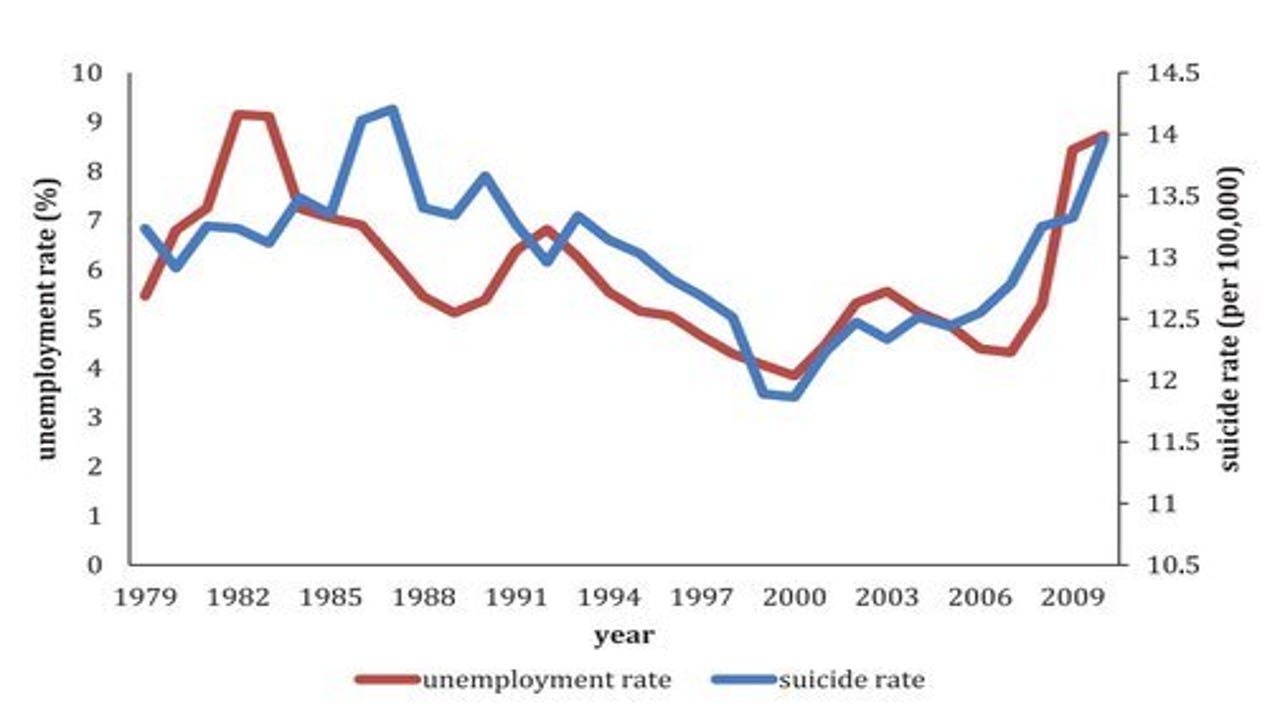
Considering mental illness an individual chemico-biological problem has enormous benefits for capitalism. First, it reinforces Capital’s drive towards atomistic individualization (you are sick because of your brain chemistry). Second, it provides an enormously lucrative market in which multinational pharmaceutical companies can peddle their pharmaceuticals (we can cure you with our SSRIs). It goes without saying that all mental illnesses are neurologically instantiated, but this says nothing about their causation. 18
CHEMICAL OR SOCIAL PROBLEMS?
The dissemination of pharmaceutical products has been a windfall for Big Pharma. For example, it is arguable that the now debunked “chemical imbalance theory” of depression that was promoted to sell Prozac was the most successful marketing campaign in human history. Even if low serotonin is the culprit for major depression this explanation says nothing of causation. Depression is an absence of vitality and pleasure, which is libidinal (emotional) energy of the whole body, not isolated in the brain.
Robert Whitaker (2010) found evidence that pharmaceutical interventions create an “iatrogenic” effect: the treatment causes or creates the illness. Psychiatric drug treatment creates a chronicity of illness (repeated episodes) versus remission of symptoms. The person’s body becomes increasingly dependent on the drug and decreasingly self-regulating. This is good for business if the long-term treatment of psychotropics medication keeps the person sick. Then they increasingly rely on the sick-making-drugs that keep making them sick.

Whitaker (2010) states how over the course of decades, “the psychiatric establishment has told us a false story. It told us that schizophrenia, depression, and bipolar illness are known to be brain diseases,” despite the lack of “any scientific studies that document this claim.” He continues that psychiatry “told us that psychiatric medications fix chemical imbalances in the brain.”
Most important of all, the psychiatric establishment failed to tell us that the drugs worsen long-term outcomes. 19
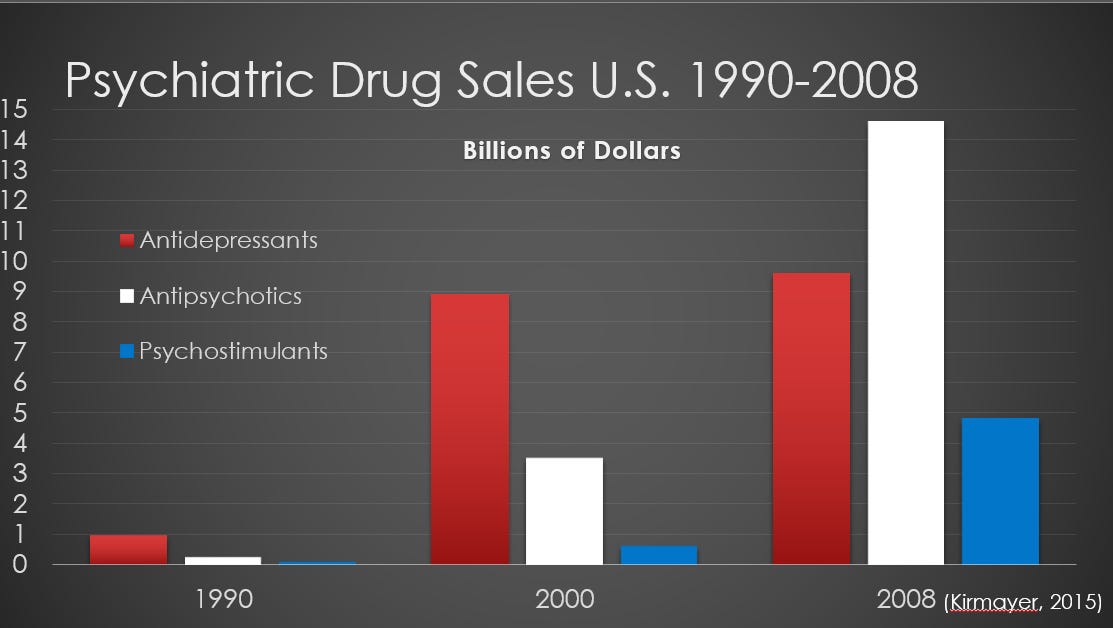
Believe it or not, the more advertising dollars spent by pharmaceutical companies, the higher the rates of prescriptions. For example, during the period of 1996 to 2001, spending on advertising ($7.9 billion) more than doubled to $15.4 billion. Prescriptions for antidepressant and antipsychotic medication in 1991 was 50 million, “but by 1998 that number rose to almost 134 million.” Sales for all psychotropic medications went from $2.5 billion in 1990 to $15 billion in 1999.20

In the 2007 book The Loss of Sadness, Horowitz and Wakefield note how “the discipline of psychiatry itself is now thoroughly enmeshed with the corporate culture of this industry.” 21 The U.S. red (antidepressants), white (antipsychotics) and blue (psychostimulants) sales of psychiatric drugs are seen in the graph below. Of note, direct-to-consumer advertising was approved by the FDA in 1997 (notice the bump in the graph at 2000). The U.S. and New Zealand are the only countries in the world that allow DTC ads. Sales have boomed in large part because patients are allowed to solicit their doctors for specific drugs they see online and on television.
The other groundless claim is a genetic causal mechanism for attention deficit and hyperactive disorder (ADHD). Why are more boys being diagnosed with ADHD, especially at the onset of kindergarten? 22 The DSM diagnosis of ADHD is understood as an issue with the dopaminergic system in the brain. This explanation is great for companies that sell Adderall. The stimulant medication is said to be a lifelong need for these individuals. However, the treatment of ADHD suppresses the excess libidinal energy of the rambunctious child. Stimulants—and we are talking about methamphetamine derivatives—pacify the child through the numbing of emotional (sexual) energy.
PRIVATIZING & PROFITING
Fisher (2009) is again correct in the effect of isolating the individual and then further isolating the pathology as inside their head (brain):
By privatizing these problems – treating them as if they were caused only by chemical imbalances in the individual’s neurology and/or by their family background – any question of social systemic causation is ruled out. 23
The rhetorical question is always, who benefits? This is the intersection that Mark Fisher guided us to:
strictly biological claims of the causes of mental health problems + apolitical definitions of those disorders (DSM) = careerism and massive profits for the capitalist system, e.g., American psychiatry and Big Pharma.
This is also a cyclical equation because increased advertising (and lobbying) by Big Pharma pumps money and information into the system that reifies the notion that the issue is with one’s neurobiology. This negates any casual mechanism that would implicate the capitalist system on our “mental health.”
Big Pharma and American psychiatry use studies and advertising campaigns with biological claims (and solutions) for mental health problems + apolitical definitions of those disorders (DSM) = profits for the capitalist system and social control/pacification of the citizens
There is no antipsychiatry movement like in the 1960s. Therefore, there is no alternative “reality” within the above equations: psychiatric realism. The underlying message is, “Don’t change the system, work on and change your self (brain).” 24
p. x, Metzl, J. (2009). The protest psychosis. How schizophrenia became a black disease. Boston: Beacon Press.
I first came across the word “instantiation” reading Fisher’s book. I did not know the meaning, so I looked it up. The word “instantiate” means to represent (an abstraction) by a concrete instance. Whatever the fuck that means. I think of instantiation as distinct yet not-separate. As analogy, consider a tattoo. We call a bunch of patterned ink as a “thing” but only by conceptual abstraction, i.e., it is not separated from the skin/body of the person, but you can call it a “tattoo” (darkened ink). The ink is indelible and instantiated like capitalist reality.
What Freud got right and got wrong was that what he experienced clinically: we have always been sexual beings in the sense of libidinal energy (life force). What he got wrong was that the Oedipus Complex (repression) occurs not in “reality,” but because of the transition from matriarchal structures to patriarchal ones (capitalism). The latter created and sustains the taboo of childhood and adolescent sexuality as well as into adulthood, e.g., sex is for procreation (sex-negating). Matriarchal societies had it that mother was right. Sexuality was free and there was no compulsive monogamy. Usually the “biological father” was unknown. The transition from matriarchy to patriarchy was an economic one. When marriage became profitable and tied to ownership, societies transitioned to patriarchy. The capitalist patriarchal structure became that father was right. Women became possessions and were bought in sold via a marriage “gift” by family members.
I stopped applying the DSM more than 10 years ago. The diagnoses are only used under situations where it directly benefits (usually financially) the patient, e.g., health insurance reimbursement, disability assessment, medical leave of absence, academic issues, Emotional Support Animal for renters, etc.
Gaines, A. D. (1992). From DSM-I to III-R: Voices of self, mastery and the other: A cultural constructivist reading of U.S. psychiatric classification. Social Science & Medicine, Vol 35(1), 3-24: http://dx.doi.org/10.1016/0277-9536(92)90115-7
p. 16, ibid.
p. 57, Metzl, J. (2009). The protest psychosis. How schizophrenia became a black disease. Boston: Beacon Press.
“[Task Force Head] Robert Spitzer thereupon drew up a compromise proposal: to delete the word “homosexuality” from DSM-II, where it was the first diagnosis under “Sexual deviations,” and replace it with “sexual orientation disturbance,” which would apply only to homosexuals who were unhappy with their lives as gay individuals and who sought psychiatric help.” (Decker, 2013; p. 32)
Recall that Freud and Carl Jung both acquiesced to the German Nazis to save the “scientific” psychoanalysis. People such as Wilhelm Reich, MD were seen as trouble-makers for calling out fascism for what it was in the 1930s. Freud wanted to make concessions with the Nazis. Now, in the name of “mental health,” most clinicians are welcoming the regime of global capitalism.
p. 19, Gaines, A. D. (1992). From DSM-I to III-R: Voices of self, mastery and the other: A cultural constructivist reading of U.S. psychiatric classification. Social Science & Medicine, Vol 35(1), 3-24: http://dx.doi.org/10.1016/0277-9536(92)90115-7
“A structured interview is an interview format worked out in advance so as to ask exactly the same questions of a group of selected patients, to achieve greater reliability in diagnosis. Spitzer, together with the Columbia psychologist Jean Endicott, had already formulated DIANGO, a computer program for psychiatric diagnosis, Spitzer having studied Fortran IV at IBM.” (Decker, 2013, p. 82)
p. 9, Gaines, A. D. (1992). From DSM-I to III-R: Voices of self, mastery and the other: A cultural constructivist reading of U.S. psychiatric classification. Social Science & Medicine, Vol 35(1), 3-24: http://dx.doi.org/10.1016/0277-9536(92)90115-7
p. 184, Decker, H.S. (2013). The making of DSM-III®: A diagnostic manual's conquest of American psychiatry. Oxford University Press: New York.
Archer, A.J. (2013). Pleading insanity. Bloomington, IN: Archway Publishing.
Emily Martin (2007) noted how the phenomenon of bipolar disorder episodes are adaptive consequences to the chaotic booms and busts of the contemporary “free market”. For example, the frenetic and not yet psychotic energy of hypomania chases a bull market while major depressive episodes fit with the hibernation of a bear market: “Closely connected to ideas about the market, manic depression morphs into bipolar disorder and comes to serve as a focal point for collective disquiet about why exhilarating highs and frightful lows seem to be inescapably intertwined in contemporary life” (Martin, 2007; p. 29).
p. 19, Gaines, A. D. (1992). From DSM-I to III-R: Voices of self, mastery and the other: A cultural constructivist reading of U.S. psychiatric classification. Social Science & Medicine, Vol 35(1), 3-24: http://dx.doi.org/10.1016/0277-9536(92)90115-7
p. 37, Fisher, M. (2009). Capitalist realism: Is there no alternative? Zero Books: UK.
p. 358, Whitaker, R. (2010). Anatomy of an epidemic: Magic bullets, psychiatric drugs, and the astonishing rise of mental illness in America. New York: Crown Publishers.
Martin, E. (2007). Bipolar expeditions: Mania and depression in American culture. Princeton: Princeton University Press.
Horwitz, A. V., & Wakefield, J. C. (2007). The loss of sadness: How psychiatry transformed normal sorrow into depressive disorder. Oxford: Oxford University Press.
Frequently, when I observe and analyze individuals with the diagnose of ADHD, what is witnessed is an attempt to receive social recognition. The person is often the “class clown,” which provides attention. Usually, they are a Daydreamer who relies on negative attention. One way to achieve this is by playing Kick Me. Therefore, an analysis of relational dynamics provides a framework for comprehension of the etiology of pathology, which exists in the social. The benefit of this explanation—aside from not needing chemical tranquilization for the rest of their life—is that the person is able to have agency over their problems. They are no longer the victims of faulty neurotransmitters. But that is not good for business.
p. 21, Fisher, M. (2009). Capitalist realism: Is there no alternative? Zero Books: UK.
The mantra of neoliberalism.